Ceramic veneers represent a highly minimally invasive treatment option for restoring teeth, offering both aesthetic and functional benefits. When proper planning, precise tooth preparation, and meticulous bonding protocols are followed, ceramic veneers have been shown to deliver years of reliable and excellent clinical performance.


Fig.1
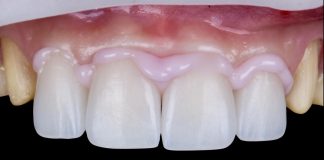
Frontal view of a 34-year-old patient with existing 12-year-old veneers, a congenitally missing lateral incisor, and an extracted canine.

Fig.2
The patient reported excessive gingival display, an unaesthetic bridge on teeth 12 and 13, mild diastema, and gingival recession with visible root surfaces.

Fig.3
Digital planning was performed to modify the shape, volume, and form of the teeth. The patient was also advised to undergo Botox treatment to reduce upper lip elevation and address the gummy smile—particularly in the region of tooth 13, where thin gingival tissue revealed a grayish discoloration from the underlying implant.

Fig.4
The implant was positioned close to the free gingival margin, significantly limiting both abutment design and soft tissue contouring options.

Fig.5
A mock-up was created based on the digital design to confirm the volume, size, and position of the final prosthesis.

Fig.6
The old veneers were carefully removed to preserve the tooth structure. A double cord technique with Kerr retraction cords (Kerr Corporation, Orange, California, USA) was used for optimal gingival management.

Fig.7
PickPack (Pascal, Belo Horizonte, Brazil), a highly effective instrument for packing retraction cords, was used during this process.

Fig.8
A precise VPS impression was made using light body and putty impression materials (Kerr Corporation, Orange, California, USA). Temporary veneers and a two-unit bridge were placed while the final restorations were being fabricated in the lab.

Fig.9
The final prostheses were tried in, and then treated using Veneer ME, a highly useful tool for step-by-step preparation of the veneers.

Fig.10
The ceramic type used for these veneers is feldspathic. Proper surface treatment is crucial; for feldspathic ceramics, etching is done with hydrofluoric acid for 90 seconds. The sequence of preparing the surface is outlined in the diagram below.

Fig.11
An open dam was applied for adequate isolation, and the cement used was NX3 Nexus™ (Kerr Corporation, Orange, California, USA) light-curable clear shade cement, chosen for its excellent handling, shade stability, and long-term bond strength.

Fig.12
A total-etch technique was employed after air abrasion of the tooth surface with 27-micron aluminum oxide. OptiBond™ Universal (Kerr Corporation, Orange, California, USA) was used as the bonding agent of choice.


Fig.13
The veneers were bonded starting with the two central incisors, followed by the remaining veneers.

Fig.14
The excess cement cleanup after achieving the flash is performed in different steps:
1. Using a brush when the cement is in gel form and has not yet polymerized. Due to its viscous yet highly thixotropic nature, most excess cement can be easily removed at this stage.

Fig.15
2. Use Eccesso (LM Dental, Parainen,Finland) to remove any remaining excess after spot polymerization.

Fig.16
After the initial cleanup and cement setting, the restoration is covered with a liquid glycerine gel and polymerized for 30 seconds, starting from the palatal side and then the buccal side in three planes.

Fig.17
3. A 15-number surgical blade is used to remove any remaining excess, ensuring no exposed resin is left behind.

Fig.18
A metal proximal strip is used to ensure no interproximal cement remains.

Fig.19
The two-unit bridge was screw-retained. To enhance aesthetics, an illusion of a papilla was created between the pontic on tooth 12 and the retainer on tooth 13. The size, volume, and final form of the veneers were redefined. The final restorations resulted in a fuller and more pleasant smile.

Fig.20
Final situation.
Conclusions
The use of appropriate protocols and materials ensures a treatment outcome that delivers exceptional aesthetics, with a well-integrated restoration that exhibits no postoperative sensitivity and long-term success.
Bibliography
- Ajay Juneja https://www.styleitaliano.org/no-prep-and-minimal-prep-veneers/
- Gilbert Jorquera https://www.styleitaliano.org/complete-digital-work-flow-for-laminate-veneers/
- Strasseler HE. Minimally invasive porcelain veneers: indications for a conservative esthetic dentistry treatment modality. Gen Dent. 2007:55(7):686-694.
- Javaheri D. Considerations for planning esthetic treatment with veneers involving no or minimal preparation. J Am Dent Assoc. 2007:138(3):331-337.
- Calamia JR. Etched porcelain facial veneers: a new treatment modality based on scientific and clinical evidence. N Y J Dent. 1983:53(6):255-259.
- Calamia JR, Calamia CS. Porcelain laminate veneers: Reasons for 25 Years of success. Dent Clin N Am 2007:51: 399-417.